
The blog of Freedom and Individual Rights in Medicine (FIRM)
Thursday, January 31, 2019
Hsieh Forbes Column: "Should Doctors Google Their Patients?"
My latest Forbes piece is now out: "Should Doctors Google Their Patients?".


Tuesday, January 8, 2019
Law Of The ER
Rada Jones, MD: "68 laws of the ER".
I, of course, liked:
I, of course, liked:
64. Sage's First Advice: Skip the CT if the patient with abdominal pain is eating McDonald's.
Thursday, December 27, 2018
Hsieh Forbes Column: "So You Got A Consumer DNA Test For Christmas -- Now What?"
My latest Forbes column is now out: "So You Got A Consumer DNA Test For Christmas -- Now What?"
I discuss some unintended consequences of direct-to-consumer DNA testing, as well as the growing use of publicly available genetic data bases for tracking people.

I discuss some unintended consequences of direct-to-consumer DNA testing, as well as the growing use of publicly available genetic data bases for tracking people.
Thursday, November 29, 2018
Hsieh Forbes Column: "Could #MeToo Hurt Women's Health Care?"
Even good movements can create bad unintended consequences. My latest column in Forbes asks: "Could #MeToo Hurt Women's Health Care?"
I discuss recent research that fears of false accusations of sexual assault could prevent men from giving life-saving CPR to women in cardiac arrest.

I discuss recent research that fears of false accusations of sexual assault could prevent men from giving life-saving CPR to women in cardiac arrest.

Monday, October 29, 2018
Hsieh Forbes Column: When Government-Backed 'Nudgers' Go Bad
My latest Forbes piece is now out: "When Government-Backed 'Nudgers' Go Bad".
I discuss how bad science and bad government policy may have affected the diets of millions of American school children.

I discuss how bad science and bad government policy may have affected the diets of millions of American school children.

Monday, October 1, 2018
Hsieh Forbes Column: The Promise And Perils Of New Apple Watch Medical Technologies
My latest Forbes piece is now up: "The Promise And Perils Of New Apple Watch Medical Technologies".
Monday, August 13, 2018
Hsieh Forbes Column: How Licensing Laws Harm Mothers, Infants, And Lactation Consultants
My latest Forbes column is now out: "How Licensing Laws Harm Mothers, Infants, And Lactation Consultants".
I discuss the new law in the state of Georgia mandating licensure of lactation consultants, and how that harms minority and low-income mothers and babies.
Fortunately, the Institute For Justice is on the case, fighting this unjust law.
More details at, "How Licensing Laws Harm Mothers, Infants, And Lactation Consultants".

I discuss the new law in the state of Georgia mandating licensure of lactation consultants, and how that harms minority and low-income mothers and babies.
Fortunately, the Institute For Justice is on the case, fighting this unjust law.
More details at, "How Licensing Laws Harm Mothers, Infants, And Lactation Consultants".
Monday, July 30, 2018
Hsieh Forbes Column: Why The Idea Of Single Payer Heath Care Won't Die
My latest Forbes column discusses how "single payer" health care keeps being rejected at the state level — often by Democrats.
Yet it keeps coming back, like a political zombie: "Why The Idea Of Single Payer Heath Care Won't Die."
Related piece by Steve Forbes: "Only Free Markets Will Save — And Strengthen Healthcare".

Yet it keeps coming back, like a political zombie: "Why The Idea Of Single Payer Heath Care Won't Die."
Related piece by Steve Forbes: "Only Free Markets Will Save — And Strengthen Healthcare".

Friday, June 29, 2018
Hsieh Forbes Column: Doctors Need To Shut Up More
In which I put on my Grumpy Old Man hat and complain about other doctors, "Doctors Need To Shut Up More". My latest in Forbes.
#GetOffMyLawn #HLMenckenIsMySpiritAnimal
#GetOffMyLawn #HLMenckenIsMySpiritAnimal
Monday, June 25, 2018
Hsieh WSJ Column On Doctors And Guns
I am honored and delighted to have been invited by the Wall Street Journal to write a column on the topic, "Should Doctors Routinely Talk to Patients About Gun Use?".
They invited two physicians to take opposite sides, with Dr. Megan L. Ranney of Brown University taking the "yes" side and myself taking the "no" position. Many thanks to all who helped provide quotes!
(I know that some readers might not be able to read the full piece because of the paywall. I'll see if I can post screenshots or excerpts of my piece later. You can often read the full text of the piece by searching for the title on Twitter and then viewing the piece through the Twitter link -- for example via this Tweet by Ari Armstrong.)
The link to the pair of pieces can be found here.

Monday, May 14, 2018
Hsieh Forbes Column: "Pelvic Exams On Anesthetized Women Without Consent: A Troubling And Outdated Practice"
My latest Forbes column is now out -- "Pelvic Exams On Anesthetized Women Without Consent: A Troubling And Outdated Practice".
Many doctors think this is "no big deal" and "good for society", whereas many patients consider this a violation.
Ultimately, the patients' wishes should prevail.

Many doctors think this is "no big deal" and "good for society", whereas many patients consider this a violation.
Ultimately, the patients' wishes should prevail.

Monday, April 30, 2018
Hsieh Forbes Column: That Time The CDC Asked About Defensive Gun Uses
My latest Forbes piece is now out: "That Time The CDC Asked About Defensive Gun Uses".
I discuss some recent work by criminologist Gary Kleck on unpublished CDC data on defensive gun use, and how that may support the case of gun rights advocates.
Some of the statistical evidence is still in question, however, and Kleck has withdrawn the original version of his paper pending further analysis.
Ultimately, individual rights are not validated (or refuted) by statistics. But real-world evidence can help affirm the underlying principles.
I also wanted to note one good response I received from Ari Armstrong, responding to a point I made in my piece: "I think there are probably fewer defensive gun uses than in the '90s, simply because violent crime has gone down so there's less need for defense."
For more details, see the full text of "That Time The CDC Asked About Defensive Gun Uses".
Related articles:
"Any Study Of ‘Gun Violence’ Should Include How Guns Save Lives" (Paul Hsieh, 3/20/2018)
"Criminologist Gary Kleck on Guns, Crime, and Their Study" (Ari Armstrong, 11/7/2015)
Tuesday, March 20, 2018
Hsieh Forbes Column: Any Study Of 'Gun Violence' Should Include How Guns Save Lives
My latest Forbes column is now out: "Any Study Of 'Gun Violence' Should Include How Guns Save Lives".
I discuss three key principles that should be included in any kind of "gun violence" research, including:
Any public health research that studies only the negative effects of criminal misuse of guns while ignoring the positive lawful uses misses a critically important part of the picture.

I discuss three key principles that should be included in any kind of "gun violence" research, including:
- Firearms save lives as well take lives.
- The value of firearms in the hands of law-abiding citizens should be measured in terms of lives saved or crimes prevented, not criminals killed.
- The right to self-defense does not depend on statistics and numbers.
Any public health research that studies only the negative effects of criminal misuse of guns while ignoring the positive lawful uses misses a critically important part of the picture.
Thursday, February 22, 2018
Hsieh Forbes Column: Hollywood Vs. Reality in Medicine
My latest Forbes column is now out: "How Badly Does Hollywood Distort Truth In Medical Dramas?"
I discuss some recent research on television representations of trauma and emergency medical care, and how differences between TV and reality can affect both patients and doctors.
I like a good medical drama as well as anyone, but sometimes the mistakes make me cringe. Of course, anyone who has watched a medical TV drama with me and has had to "shush" me when I repeatedly complain about some Hollywood exaggeration already knows this.
(And don't even get me started about random x-rays being hung upside down or backwards on viewboxes in the background of an OR or ER scene.)
Friday, January 26, 2018
Hsieh Forbes Column: You Might Not Like The President, But That Doesn't Mean He's Crazy
My latest Forbes column is out: "You Might Not Like The President, But That Doesn't Mean He's Crazy".
I discuss the latest push by some psychiatrists to declare the President unfit to hold office on mental health grounds. And the response of the White House physician who examined the President, including a cognitive evaluation.
As Dr. Jeffrey Lieberman, Chairman of the Department of Psychiatry, Columbia University College of Physicians and Surgeons, wrote in the New England Journal Of Medicine:
Psychiatry has made too many past missteps to engage in political partisanship disguised as patriotism — witness its collusion in Nazi eugenics policies, Soviet political repression, and involuntary confinement in mental hospitals of dissidents and religious groups in the People’s Republic of China. More than any other medical specialty, psychiatry is vulnerable to being exploited for partisan political purposes and for bypassing due process for establishing guilt, fault, and fact.
Friday, December 29, 2017
Hsieh Forbes Column: The War On Meat
My final Forbes column of the year is now out: "In The War On Meat, Count Me In The Resistance".
I discuss the latest idea of a "tax on meat", and why that's bad from both a medical and public policy perspective.
To (mis)quote Firefly, "I don't care. I'm still free. You can't take my bacon from me."
Happy New Year, everyone!

I discuss the latest idea of a "tax on meat", and why that's bad from both a medical and public policy perspective.
To (mis)quote Firefly, "I don't care. I'm still free. You can't take my bacon from me."
Happy New Year, everyone!

Monday, November 27, 2017
Hsieh Forbes Column: Will Computers Be Reading Your Chest X-Ray?
My latest Forbes column is now out: "Will Computers Be Reading Your Chest X-Ray?"
A team of researchers from Stanford University department of Computer Science and Stanford Medical School have now created an AI system capable of diagnosing pneumonia on chest x-rays more accurately than skilled human radiologists.
The future is coming quickly.
[Image below from the original article: "Our model, CheXNet, is a 121-layer convolutional neural network that inputs a chest X-ray image and outputs the probability of pneumonia along with a heatmap localizing the areas of the image most indicative of pneumonia."]

Monday, October 30, 2017
Hsieh Forbes Column: "Help Patients By Allowing More Telemedicine"
My latest Forbes piece is now out: "Help Patients By Allowing More Telemedicine".
I discuss the growing use of telemedicine to allow doctors to connect to patients remotely, and how we can reduce regulatory barriers to wider adoption. This is a great use of 21st-century technology that can help patients.

I discuss the growing use of telemedicine to allow doctors to connect to patients remotely, and how we can reduce regulatory barriers to wider adoption. This is a great use of 21st-century technology that can help patients.

Monday, September 25, 2017
Hsieh Forbes Column: "Pagers, AI, And Google"
My latest Forbes piece is now out, "Pagers, AI, And Google: 3 Tales Of Technology And Medicine".
I discuss some unexpected wrinkles with old tech, new tech, and current tech in health care.
I remember back in the 1990s, when everyone cool had one of these.

I discuss some unexpected wrinkles with old tech, new tech, and current tech in health care.
I remember back in the 1990s, when everyone cool had one of these.
Tuesday, August 29, 2017
Hsieh Forbes Column: Changing Consent Rules For Organ Donation?
My latest Forbes piece is now up: "Should The Government Require Your Consent To Be An Organ Donor?"
I discuss some controversial proposed changes to loosen the consent process for organ donation, including the pros and cons. There are a lot of passionate advocates on both sides of this debate, and I tried my best to treat each position as fairly as possible (even though I do favor one side).

I discuss some controversial proposed changes to loosen the consent process for organ donation, including the pros and cons. There are a lot of passionate advocates on both sides of this debate, and I tried my best to treat each position as fairly as possible (even though I do favor one side).
Saturday, July 8, 2017
Hsieh Forbes Column: Charlie Gard Case, Summarized In 30 Words
My latest in Forbes: "Charlie Gard Case, Summarized In 30 Words". Plus a glimmer of hope for the family.
Thursday, June 29, 2017
Hsieh Forbes Column: Three Novel Health Care Innovations
My latest Forbes column is now out: "Three Novel Health Care Innovations".
Drones! Photosynthesis! AI!
Read more details at "Three Novel Health Care Innovations".
From one linked article:

Drones! Photosynthesis! AI!
Read more details at "Three Novel Health Care Innovations".
From one linked article:
"This medical drone can deliver an automated external defibrillator to a patient who has suffered a sudden cardiac arrest. In tests, the drone arrived more than 16 minutes faster than an ambulance had."
Monday, May 22, 2017
Hsieh Forbes Column: 3 Big Questions About AI-Guided Medicine
My latest Forbes piece is out, continuing last month's theme on artificial intelligence in medicine. It's entitled, "3 Big Questions About AI-Guided Medicine".
In particular, the three questions are:
1. Who will control (and have access to) individual patient data?
2. Will we know how the AIs arrive at their diagnoses and recommendations?
3. What will the AIs optimize for?
For more details on each, see the full text of "3 Big Questions About AI-Guided Medicine".
Sunday, April 30, 2017
Hsieh Forbes Column: "AI In Medicine: Rise Of The Machines"
My new Forbes column is now out: "AI In Medicine: Rise Of The Machines".
If current trends continue, medical care change over the next 20 years just as much as internet has changed life between 1997 and today.
If current trends continue, medical care change over the next 20 years just as much as internet has changed life between 1997 and today.
Friday, March 31, 2017
Hsieh Forbes Column: Doctors Should Not Record Immigration Status Nor Gun Ownership
My latest Forbes column is now out: "Doctors Should Not Record Immigration Status Nor Gun Ownership In Patient Charts".
Patients routinely disclose sensitive personal data to their physicians. Doctors can and should be mindful of information that might someday be used against their patients by unscrupulous government authorities.
In particular, with increasing use of electronic medical records that can be data-mined by those with access, physicians can help protect the doctor-patient relationship by leaving some information out of the records.
Related earlier piece, “Why Doctors Should Not Ask Their Patients About Guns.”
Monday, February 27, 2017
Hsieh Forbes Column: People Confound Experts: Three Paradoxes Of Health And Human Behavior
My latest Forbes column is now out, "People Confound Experts: Three Paradoxes Of Health And Human Behavior".
I discuss three counter-intuitive or paradoxical results from recent health policy research, in which patients don't respond in the way that experts might have predicted.
For example: If you have a serious heart problem, you might do better if the top cardiologists are out of town.
For more details, see the full piece, "People Confound Experts: Three Paradoxes Of Health And Human Behavior"!
Monday, January 30, 2017
Hsieh Forbes Column: Health Freedom For Everyone, Not Just Women
My latest Forbes column is now out, "Health Freedom For Everyone, Not Just Women".
My basic theme is that free-market reforms (not government-run health care) will best protect our medical freedoms.
From the article:

My basic theme is that free-market reforms (not government-run health care) will best protect our medical freedoms.
From the article:
I support abortion rights and reproductive freedom rights. I love that many participants in the marches don’t want the government dictating which medical procedures women may or may not receive.For more details, see the full text of "Health Freedom For Everyone, Not Just Women".
I also hope that people recognize that government-run health care will inevitably mean government controlling which medical procedures patients may or may not receive. Whenever “somebody else” pays for your health care, inevitably “somebody else” will decide what health care you do (or do not) receive.
Tuesday, January 10, 2017
The Evolution Of Radiology
Dr. James Chang: "The evolution of radiology".
Yup, this seems about right! (Click on image to see full size version.)

Yup, this seems about right! (Click on image to see full size version.)

Thursday, December 29, 2016
Hsieh Forbes Column: No, The Government Should Not Provide Health Insurance For All Americans
My latest Forbes piece is now out, "No, The Government Should Not Provide Health Insurance For All Americans".
I discuss a proposal from conservative health policy analyst James Capretta in which he argues, "The GOP Should Provide Health Insurance for All Americans". And I propose some alternative free-market approaches that we can start implementing in 2017.
For more details, see the full text of "No, The Government Should Not Provide Health Insurance For All Americans".
And Happy New Year to all our supporters and subscribers!
Monday, November 28, 2016
Hsieh Forbes Column: UK Vs US Aortic Aneurysm Deaths
My latest Forbes pieces is now out: "Patients With Aortic Aneurysms More Likely To Die In The UK Than The US".
I discuss a recent New England Journal of Medicine study which showed that if you have an abdominal aortic aneurysm (aka "AAA") in the US vs the UK, the UK patients have to wait longer for surgery, and the aneurysms don't get repaired until they are larger (and more at risk of rupture.)
The researchers conclude: "Rates of aneurysm rupture and aneurysm-related death were significantly higher in England than in the United States".
I also cover three natural follow-up questions:
1) Were US surgeons jeopardizing their patients by operating more aggressively than UK surgeons?
2) Did the UK nationalized health system contribute to the lower rates of appropriate surgery in the UK?
3) Will US government policies incentivize American surgeons towards more — or less — appropriate treatments?
For more details, read the full text of "Patients With Aortic Aneurysms More Likely To Die In The UK Than The US".
Tuesday, October 25, 2016
Hsieh Forbes Column: How Your Doctor's Politics Affects Your Health Care
My latest Forbes piece is now out, "How Your Doctor's Politics Affects Your Health Care -- And What You Can Do About It".
I discuss the latest research indicating the doctors' own personal political biases can affect the advice they give patients in three areas -- abortion, gun ownership, and marijuana use. And strategies that patients and doctors can adopt to minimize inappropriate physician bias in the exam room.

I discuss the latest research indicating the doctors' own personal political biases can affect the advice they give patients in three areas -- abortion, gun ownership, and marijuana use. And strategies that patients and doctors can adopt to minimize inappropriate physician bias in the exam room.
Friday, September 16, 2016
Hsieh Forbes Column: No, There's No 'Smoking Gun' in Clinton's Doctor Letter
I have a new short Forbes piece out now, discussing a couple of issues related to Hillary Clinton's health: "No, There's No 'Smoking Gun' in Clinton's Doctor Letter".
tldr; Clinton's opponents should concentrate on her bad public policy positions, not her medical record.
tldr; Clinton's opponents should concentrate on her bad public policy positions, not her medical record.
Monday, August 29, 2016
Hsieh Forbes Column: How Government Quality Guidelines Hurt Transplant Patients
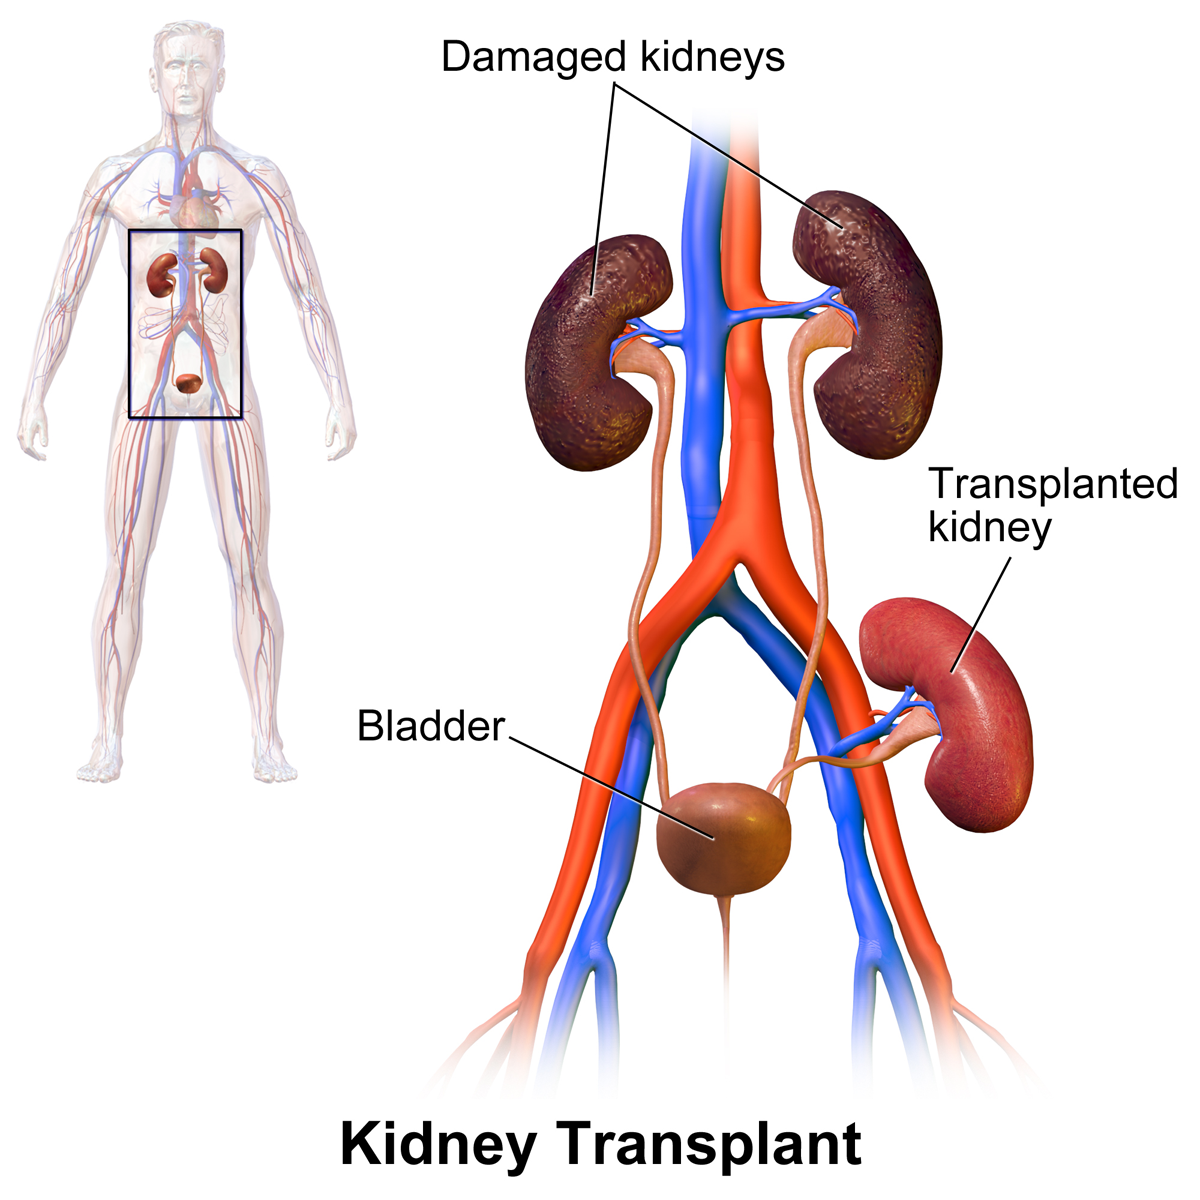
My latest Forbes piece is now up: "How Government Quality Guidelines Hurt Transplant Patients".
I discuss how federal government "quality guidelines" created perverse incentives to deny medical care to the sickest patients.
In particular, many transplant centers started dropping the sickest patients from their transplant waiting lists in order to keep their success rates up. Plus many hospitals rejected less-than-perfect organs out of fear of harming their federal government score cards.
As transplant surgeon Dr. Adel Bozorgzadeh said:
For more details, read the full text of "How Government Quality Guidelines Hurt Transplant Patients".
(Related piece: "Doctor ‘Report Cards’ May Be Hazardous To Your Health.")
I discuss how federal government "quality guidelines" created perverse incentives to deny medical care to the sickest patients.
In particular, many transplant centers started dropping the sickest patients from their transplant waiting lists in order to keep their success rates up. Plus many hospitals rejected less-than-perfect organs out of fear of harming their federal government score cards.
As transplant surgeon Dr. Adel Bozorgzadeh said:
“If you have young guy who has a 100 percent chance of dying, but only a 30 percent chance of dying with a transplant, you would say, ‘What the hell, give the guy a chance,’” even if the operation might be risky, he said. “But if I make an argument like that, I will be under pressure from all these other stakeholders who would penalize me.”The federal guidelines created a conflict of interest for hospitals, caught between their government paymasters and the patients they were supposed to care for.
For more details, read the full text of "How Government Quality Guidelines Hurt Transplant Patients".
(Related piece: "Doctor ‘Report Cards’ May Be Hazardous To Your Health.")
Tuesday, August 2, 2016
FIRM Website Problems Fixed
My deepest apologies for the recent downtime of the FIRM website. And many thanks to my ex-wife Diana Brickell for fixing the DNS issues! I should be back in action soon.
Friday, June 24, 2016

Wednesday, June 22, 2016
Hsieh Forbes Column: Why I Don't Trust Government-Backed 'Gun Violence' Research
My latest Forbes piece is now out: "Why I Don't Trust Government-Backed 'Gun Violence' Research".
I discuss the anti-gun bias at the federal government Centers For Disease Control (CDC) and why we should be suspicious of calls for more CDC-backed research into "gun violence".

I discuss the anti-gun bias at the federal government Centers For Disease Control (CDC) and why we should be suspicious of calls for more CDC-backed research into "gun violence".
Wednesday, June 15, 2016
When Everything Is "Critical", Then Nothing Is
Another consequence of poorly designed electronic medical records (EMRs) is "alert fatigue":

Electronic health records increasingly include automated alert systems pegged to patients’ health information. One alert might signal that a drug being prescribed could interact badly with other medications. Another might advise the pharmacist about a patient’s drug allergy. But they could also simply note each time that a patient is prescribed painkillers — useful to detect addiction but irrelevant if, say, someone had a major surgery and is expected to need such meds. Or they may highlight a potential health consequence relevant to an elderly woman, although the patient at hand is a 20-something man.This can have real-life consequences:
The number of these pop-up messages has become unmanageable, doctors and IT experts say, reflecting what many experts call excessive caution, and now they are overwhelming practitioners.
Clinicians ignore safety notifications between 49 percent and 96 percent of the time, said Shobha Phansalkar, an assistant professor of medicine at Harvard Medical School.
“When providers are bombarded with warnings, they will predictably miss important things,” said David Bates, senior vice president at Brigham and Women’s Hospital in Boston.
In one instance at Children’s [Hospital of Philadelphia], doctors ignored relevant information about how a patient might respond to a drug, Shelov said, because it appeared alongside heaps of other superfluous notifications — warnings, for instance, about drugs that posed minimal risk of interfering with each other. Consequently, the patient received medication that induced a potentially lethal reaction.When everything is "critical", then nothing is.
The hospital caught the mistake in time, but the incident spurred a series of changes. A team of pharmacists, doctors and other clinicians have sorted through what triggered alerts in their system, turning off the ones they decided weren’t actually relevant or necessary. That has helped. But it’s still an ongoing battle, Shelov said. “It’s a little bit of trying to turn off the firehose.”
Monday, June 13, 2016
Doctors And Handwashing
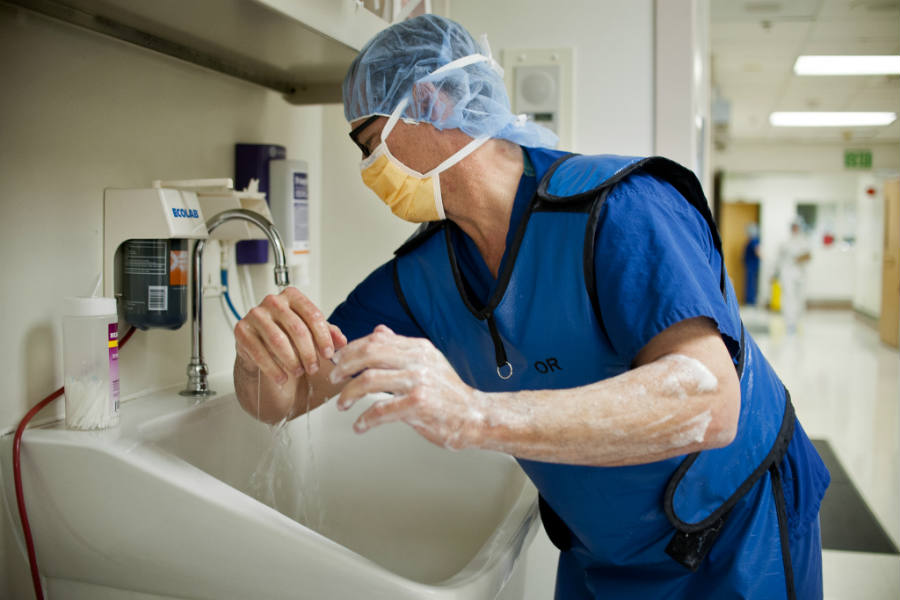
"What is doctors' compliance rate for hand hygiene procedures?"
As Tyler Cowen says:
As Tyler Cowen says:
According to a new study, when they know they are being watched it is 57 percent.
When they don’t know they are being watched, it is 22 percent.
What I find shocking is not the difference, which fits readily into the economic way of thinking. It is that direct observation of doctors still does not get the rate above 57 percent.
Tuesday, May 31, 2016
Hsieh Forbes Column: Three Tales of Health, Technology, and Freedom
My latest Forbes piece is now out: "Three Tales of Health, Technology, and Freedom".
I highlight recent stories on the "artificial pancreas", research into Chronic Fatigue Syndrome, and patients ordering their own blood tests.
When people pursue important health goals, often the government helps best by getting out of the way.
I highlight recent stories on the "artificial pancreas", research into Chronic Fatigue Syndrome, and patients ordering their own blood tests.
When people pursue important health goals, often the government helps best by getting out of the way.
Friday, May 13, 2016
Dad Of The Year
From the Wall Street Journal, "Tech-Savvy Families Use Home-Built Diabetes Device":
Third-grader Andrew Calabrese carries his backpack everywhere he goes at his San Diego-area school. His backpack isn’t just filled with books, it is carrying his robotic pancreas.Unfortunately, the FDA isn't particularly supportive of such grass-roots endeavors.
The device, long considered the Holy Grail of Type 1 diabetes technology, wasn’t constructed by a medical-device company. It hasn’t been approved by regulators.
It was put together by his father...
Friday, April 29, 2016
Hsieh Forbes Column: Protect Physician Free Speech In The Office Visit
My latest Forbes column is now out: "Protect Physician Free Speech In The Office Visit".
Should politicians dictate what physicians must (or must not) say to patients when it comes to contentious political issues like abortion or gun ownership? I say, "no".

Should politicians dictate what physicians must (or must not) say to patients when it comes to contentious political issues like abortion or gun ownership? I say, "no".
Monday, April 25, 2016
Wednesday, April 13, 2016
Transplant Woes
An unfortunate story: "The Search For A 'Perfect' Organ Cost My Wife Her Life". (Via @motivepwr.)
Monday, April 11, 2016
Human Stories Vs. Electronic Medical Records
Dr. Susan Koven describes how, "As hospitals go digital, human stories get left behind".
Dr. Koven described an encounter with a patient, with enormously rich detail. But when she had to record the information in the electronic medical records, the system hampered her ability to tie key connections together:

Dr. Koven described an encounter with a patient, with enormously rich detail. But when she had to record the information in the electronic medical records, the system hampered her ability to tie key connections together:
My warm feelings vanished as I sat down to document the visit. While I’ve used an electronic medical record for several years, Epic, the system my hospital recently adopted, makes recording stories such as the one my patient shared especially difficult. Her grief and her fatigue, which are inseparable in reality, Epic treats as different problems. That she lives alone and there’s conflict in her extended family, which are also inextricable from her symptoms, must be filed under a tab marked “Social Documentation.”The electronic records may make life easier for the hospital billing department. And they may make life easier for researchers trying to do population-based studies. But if it hampers the primary care physician's ability to actually care for the patient, we have a problem.
Epic features lists of diagnoses and template-generated descriptions of symptoms and physical examination findings. But it provides little sense of how one event led to the next, how one symptom relates to another, the emotional context in which the symptoms or events occurred, or the thought process of the physician trying to pull together individual strands of data into a coherent narrative. Epic is not well-suited to communicating a patient’s complex experience or a physician’s interpretation of that experience as it evolves over time, which is to say: Epic is not built to tell a story...
The risk of this format, as physician and medical informatics expert Dr. Robert Wachter points out in a blog post, is that we may forget that “patients are more than the sum of their problems.”
A medical record that abandons narrative in favor of a list does more than dehumanize our patients. It also hampers a clinician’s diagnostic abilities. Take a patient I saw recently, a middle-aged woman with palpitations. She was perimenopausal, stressed out at work, having trouble sleeping, drinking lots of coffee to stay awake during the day, and had a family history of heart disease. Any one of those issues might explain her palpitations, but more likely some combination of interrelated factors was causing them. Sorting out the story is crucial to deciding which tests to order and what treatment to recommend.
Friday, April 8, 2016
Patient Secretly Records Surgery And Hears Disturbing Conversations
From the 4/7/2016 Washington Post: "Patient secretly recorded doctors as they operated on her. Should she be so distressed by what she heard?"
Although I don't do surgery, I do sometimes perform invasive procedures on unconscious or sedated patients. I always speak as if the patient were fully awake and able to understand me.
One can debate the ethics of recording one's doctor when they aren't aware of it. I do fully support recording important doctor visits with the consent of both parties, as I discussed last year in, "Why You Should Record Your Doctor Visits".
Thursday, April 7, 2016
Assisted Suicide in California
News update: "Doctor-assisted dying will be legal in California from June 9th".
I recognize this is a controversial topic amongst many physicians. However, I support the basic idea in the interests of patient autonomy.
My own thoughts on this topic can be found in this January 2015 piece, "Does Your Right To Life Include The Right To Die?"
I recognize this is a controversial topic amongst many physicians. However, I support the basic idea in the interests of patient autonomy.
My own thoughts on this topic can be found in this January 2015 piece, "Does Your Right To Life Include The Right To Die?"
Thursday, March 31, 2016
Hsieh Forbes Column on The Great Canadian Sperm Crisis
My latest Forbes piece is now up: "The Market Solution To The Great Canadian Sperm Crisis".
A couple of facts:
* There is an enormous shortage of donated sperm in Canada, such that infertile couples have to rely on (gasp) imported sperm from the US.
* The Canadian government outlaws paying Canadian sperm donors for their product.
Hmm.... Could there possibly be any connection between these two facts?
For more details, read the full text of "The Market Solution To The Great Canadian Sperm Crisis".

A couple of facts:
* There is an enormous shortage of donated sperm in Canada, such that infertile couples have to rely on (gasp) imported sperm from the US.
* The Canadian government outlaws paying Canadian sperm donors for their product.
Hmm.... Could there possibly be any connection between these two facts?
For more details, read the full text of "The Market Solution To The Great Canadian Sperm Crisis".
Tuesday, March 15, 2016
Catron Critiques Trump
David Catron of The American Spectator has a pretty harsh critique of Donald Trump's health care plan from the conservative perspective in his 3/14/2016 piece, "Trumpcare: A Hazy Plan From a Lazy Man".
From the opening of Catron's piece:

From the opening of Catron's piece:
[T]ake a minute to peruse the health care proposal he has finally cobbled together and posted on his campaign website. And, rest assured, it won’t take more than a minute to read. Trump’s “plan” consists of seven random nostrums that appear to have been hastily cribbed from conservative and libertarian websites by his various flunkies. And it confirms yet again that neither “the Donald” nor his yes men are willing to do their homework...(Catron also offers some broader commentary on Trump's campaign and isn't impressed.)
Thursday, March 10, 2016
Small Free Speech Victory
The 3/8/2016 New York Times reports, "FDA Deal Allows Amarin to Promote Drug for Off-Label Use".
This is a small but potentially important victory for drug company free speech rights. As the articles notes:
And if any companies would like to further pursue this kind of free speech fight, they should contact attorney Jim Manley of the Goldwater Institute. Manley and the Goldwater Institute have urged policy changes in this area and are exploring litigation.
(Related story from last year: "Free Speech 1, FDA 0".)
This is a small but potentially important victory for drug company free speech rights. As the articles notes:
The agreement settles a legal case between the agency and the company, Amarin, a small drug maker that sued the F.D.A. last year for the right to promote its only product, Vascepa, to a broader range of patients. In August, a federal district judge in Manhattan ruled that the F.D.A. could not prohibit Amarin from using truthful information to promote its drug, even for unapproved uses, because doing so would violate the company’s right to free speech.The final settlement is still subject to approval by the court.The agency on Tuesday downplayed the implications of the deal. In a statement, it said that the settlement applied only to the Amarin case and that its position on whether companies have a constitutional right to provide truthful information about off-label uses had not changed.But some legal and drug-safety experts said the settlement could encourage other companies to seek similar arrangements and, ultimately, have profound implications for how drug makers sell their products...
Clearly, the FDA wishes to keep the scope of this as narrow as possible. On the other hand, many free speech advocates would like to see this principle applied more broadly.
And if any companies would like to further pursue this kind of free speech fight, they should contact attorney Jim Manley of the Goldwater Institute. Manley and the Goldwater Institute have urged policy changes in this area and are exploring litigation.
(Related story from last year: "Free Speech 1, FDA 0".)
Wednesday, March 2, 2016
Patient Safety and Electronic Medical Records
A good report from Kaiser Health News on what doctors in the trenches deal with regularly: "EHRs In The ER: As Doctors Adapt, Concerns Emerge About Medical Errors".
Here's the introduction:
Imagine how user friendly your smart phones would be, if you had to buy one (rather than choosing whether or not to get one.)
Unfortunately, patients will pay the price:
Most doctors try their best take good care of their patients. It's unfortunate when government technology mandates makes that job that harder, not easier.

Here's the introduction:
The mouse slips, and the emergency room doctor clicks on the wrong number, ordering a medication dosage that’s far too large. Elsewhere, in another ER’s electronic health record, a patient’s name isn’t clearly displayed, so the nurse misses it and enters symptoms in the wrong person’s file.In other words, EHRs were rammed down the throats of doctors and hospitals, rather than being allowed to be integrated organically according to the best judgments of the end users.
These are easy mistakes to make. As ER doctors and nurses grapple with the transition to digitalized record systems, they seem to happen more frequently.
“There are new categories of patient safety errors” in emergency rooms that didn’t exist before the push to use electronic record systems, said Raj Ratwani, who researches health care safety and is the scientific director for MedStar Health’s National Center for Human Factors in Healthcare in Washington, D.C.
Spurred by the 2009 stimulus package and the 2010 health reform law, the federal government has offered hospitals financial incentives to adopt electronic health records that, among other things, will add efficiency and reduce errors by linking physicians’ patient records, and coordinating and tracking how care is delivered across the health system. Hospitals that don’t meet those standards are hit with penalties...
Imagine how user friendly your smart phones would be, if you had to buy one (rather than choosing whether or not to get one.)
Unfortunately, patients will pay the price:
The ER’s culture and pace, for instance, can amplify the risks of human error that stem from an already less user-friendly system. Think of the emergency physician who, reaching the end of a hectic 12-hour shift, looks for the record of a patient he just examined. He types in the man’s last name, clicks and writes medical instructions — not realizing that he’d accidentally pulled up the file of another patient with the same last name and similar age, who was admitted five minutes before.For now, this means patients will have to be extra-diligent in confirming that the data in their health records is accurate. And that any prescriptions or treatments they receive actually make sense.
While misidentifying patients in this way was hardly an issue before EHRs, it’s “becoming quite prevalent,” in this more digital era, Ratwani said.
Most doctors try their best take good care of their patients. It's unfortunate when government technology mandates makes that job that harder, not easier.
Monday, February 29, 2016
Open Your Heart
Great talk by Dr. Jordan Winkler: "10 Easy Steps to Open Your Heart".
Funny and informative. Really. I'm really glad I live at time this is possible. Contains slightly NSFW language. (Via B.E.)
Funny and informative. Really. I'm really glad I live at time this is possible. Contains slightly NSFW language. (Via B.E.)
Monday, February 22, 2016
Cut Health Costs By Paying Cash
The Wall Street Journal explains, "How to Cut Your Health-Care Bill: Pay Cash".
Not long ago, hospitals routinely charged uninsured patients their highest rates, far more than insured patients paid for the same services. Now, in the Alice-in-Wonderland world of health-care prices, the opposite is often true: Patients who pay up front in cash often get better deals than their insurance plans have negotiated for them.
That is partly due to new state and federal rules aimed at protecting uninsured patients from price gouging. (Under the Affordable Care Act, for example, tax-exempt hospitals can’t charge financially strapped patients much more than Medicare pays.) Many hospitals also offer discounts if patients pay in cash on the day of service, because it saves administrative work and collection hassles. Cash prices are officially aimed at the uninsured, but people with coverage aren’t legally required to use it.
Friday, February 19, 2016
Update on Edison Vs. MOC
Dr. Megan Edison gives an important update on the MOC controversy, including practical steps physicians can take to defend their autonomy.
Thursday, February 18, 2016
Hsieh Forbes Post: Liberals Against Sanders On Health Economics
I have another short post in today's Forbes: "Liberals Against Sanders On Health Economics".
Many on the political Left are speaking out against Bernie Sanders' economic and health proposals. Their objections lie primarily in the realm of economics (rather than deeper issues of the proper scope of government). But nonetheless, the pushback Sanders is getting from fellow "progressives" has surprised me.
When you've lost Paul Krugman...
Wednesday, February 17, 2016
Hsieh Forbes Column: Americans Love This Deadly Technology
My latest Forbes piece is now out: "Americans Love This Deadly Technology".
The theme: Americans are willing to accept 32,000 deaths per year as the price of freedom.
The theme: Americans are willing to accept 32,000 deaths per year as the price of freedom.
Friday, February 5, 2016
Pregnancy Warnings In US, Australia, And France
Here's a helpful chart in case you are pregnant.
(This was likely in response to the latest paternalisic federal government recommendations as reported in USA Today, "CDC: Young women should avoid alcohol unless using birth control".)

(This was likely in response to the latest paternalisic federal government recommendations as reported in USA Today, "CDC: Young women should avoid alcohol unless using birth control".)

Tuesday, February 2, 2016
Armstrong On Insurance Vs. Care
Dr. Richard Armstrong of the Docs4PatientCare Foundation has another nice column out, "Why Health Insurance doesn't equal Health Care".
Armstrong's basic thesis is simple:
(Read the full text of, "Why Health Insurance doesn't equal Health Care".)
Armstrong's basic thesis is simple:
Health insurance as commonly “understood” is not true insurance. This is one of the significant causes of our current national misunderstanding of health care financing which underlines the importance of these educational efforts.But the details are important. He traces the transformation of insurance from simple risk pooling for rare-but-expensive events to the current dysfunctional system. And in the process also discusses some solutions to our current problems, such as Direct Primary Care.
(Read the full text of, "Why Health Insurance doesn't equal Health Care".)
Sunday, January 31, 2016
Adalja Lecture: Infectious Diseases and National Security
If you live in Colorado, you might be interested in this upcoming dinner lecture by Dr. Amesh Adalja: "Infectious Diseases and National Security" (March 12, 2016). I've already purchased my ticket!
Here's the announcement and the link to register:
Here's the announcement and the link to register:
Hungry Minds Speaker Series
Food for the body. Food for the mind.
Infectious Diseases and National SecurityThis talk will discuss the intersection of infectious disease emergencies and national security, with special attention to the speaker’s experiences with the ongoing Ebola and measles outbreaks as well as bioterrorism and biowarfare. The talk will also address the field of public health, delineating the proper role of government as well as the role of experts in shaping policy and engaging with the public.
A Dinner and Talk featuring
Dr Amesh Adalja
Senior Associate, UPMC Center for Health Security
Clinical Assistant Professor, Department of Critical Care Medicine
Clinical Assistant Professor, Department of Emergency Medicine
Adjunct Instructor, Division of Infectious Diseases, Department of Medicine University of Pittsburgh Medical Center
Saturday March 12, 2016
5:00 – 9:00 PM
C.B. & Potts
6575 S Greenwood Plaza Blvd
Englewood, CO 80111
303-770-1982
Agenda
5:00 PM: Cocktails, Dinner (Cash)
7:00 PM: Announcements
7:15 PM: Talk with Q/A
Cost
Advance General Admission: $35 per person ($40 after 3/4)
At the Door General Admission: $40 per person
Seating at Head Table with Speaker (space limited): $75 ($80 after 3/4)
Please Note: Purchase does not include dinner; order directly at event
Online reservations through March 9, or at the door.

Monday, January 25, 2016
Hsieh Forbes Column on New Year's Resolutions
My latest Forbes piece is now out: "Are You Struggling To Keep Those New Year's Resolutions?"
I discuss "temptation bundling" and other techniques to keep your New Year's Resolutions. And the fact that sometimes it's ok to just break them!

I discuss "temptation bundling" and other techniques to keep your New Year's Resolutions. And the fact that sometimes it's ok to just break them!
Monday, January 18, 2016
Armstrong on Quality
Dr. Richard Armstrong asks (and answers) a critical question: "Who Determines Quality in Health Care?"
A couple of excerpts:
Interestingly, the New York Times recently published a piece by Dr. Robert Wachter with a similar theme: "How Measurement Fails Doctors and Teachers". Wachter notes:
By the way, there is lots more good commentary on health policy at the Docs4PatientCare Foundation website by Armstrong (pictured below) and others.

A couple of excerpts:
[E]verywhere you turn someone is measuring something or surveying something or requiring the reporting of metrics. Patients are flooded with satisfaction surveys, doctors are inundated with pay for performance reporting requirements, physician quality reporting systems and, soon on the horizon from the federal government, the new Merit Based Incentive System. It’s enough to make your head spin. So, just exactly what is going on?...To concretize the issue, Dr. Armstrong poses an example of a patient "Jack" who needs a hernia repair. As a surgeon, Dr. Armstrong will work conscientiously to do his best by Jack. But Armstrong notes:
An estimated $3.5 trillion moves through our health care economy yearly. It should be no surprise that those who are purchasing health care would be concerned about the quality and value of their purchase. What is problematic is this…how do you measure it? Also, how can anyone be certain that they are measuring the “correct” things?
[T]he doctor should be working for the patient. But what happens when a third party, a private insurance company or the government is the purchaser of health care on behalf of the patient consumer? We are experiencing that today in America and the confusion is becoming mind numbing for both patients and doctors...As Dr. Armstrong notes, piling on more regulations onto a flawed system based on third-party payments won't fix the underlying problem. I recommend folks read the whole piece for themselves, as I'm only scratching the surface of his discussion.
Our “system” needs to focus clearly on producing high quality physicians and surgeons who understand why Jack and his family need quality care and that ultimately we are responsible to them, the patients.
It is no surprise that those who are paying for the services expect quality and value. Maybe it would be wise for all of us to re-evaluate how we are paying instead of expanding ever more complex, confusing and expensive “quality assurance” processes.
Interestingly, the New York Times recently published a piece by Dr. Robert Wachter with a similar theme: "How Measurement Fails Doctors and Teachers". Wachter notes:
Avedis Donabedian, a professor at the University of Michigan’s School of Public Health, was a towering figure in the field of quality measurement. He developed what is known as Donabedian’s triad, which states that quality can be measured by looking at outcomes (how the subjects fared), processes (what was done) and structures (how the work was organized). In 2000, shortly before he died, he was asked about his view of quality. What this hard-nosed scientist answered is shocking at first, then somehow seems obvious.“The secret of quality is love,” he said.Our businesslike efforts to measure and improve quality are now blocking the altruism, indeed the love, that motivates people to enter the helping professions. While we’re figuring out how to get better, we need to tread more lightly in assessing the work of the professionals who practice in our most human and sacred fields.
By the way, there is lots more good commentary on health policy at the Docs4PatientCare Foundation website by Armstrong (pictured below) and others.
Thursday, January 14, 2016
Edison Vs. American Board of Pediatrics
Dr. Megan Edison has written an "Open Letter to the American Board of Pediatrics".
Here is the opening:

Here is the opening:
Dear American Board of Pediatrics:She describes the numerous pointless "hoops" that pediatricians must jump through in order to maintain their certification (MOC), as well as questionable finances by the ABP leadership. In her words:
On December 17 2015, at 3:01 in the middle of my busy day seeing patients, I voluntarily gave up my American Board of Pediatrics certification. I thought I should write this letter, hopefully preempting any more threatening emails warning me that I must pay up or lose my certification. This was not mere oversight on my part. This was purposeful...
I am sad about giving up my ABP certification. I remember the elation I felt when I passed my boards after residency. I really felt like I had accomplished something and that my certificate represented my professional educational commitment to pediatric medicine. Now, after seeing the monster that board certification has ballooned into, I’m very happy to be off the MOC hamster wheel and no longer supporting a corrupt system that punishes very good doctors and pushes our most experienced pediatricians into early retirement.Dr. Edison also offers concrete reforms that the ABP can adopt. Let's hope the ABP chooses to listen to her.
Tuesday, January 5, 2016
Rising Interest in Health Care Ministries
The Wall Street Journal describes how "More People Turn to Faith-Based Groups for Health Coverage".
I very much like the idea of voluntary mutual-aid societies to share health costs. But some regulators don't. An except:
I very much like the idea of voluntary mutual-aid societies to share health costs. But some regulators don't. An except:
Ministry officials say they aren’t offering insurance, don’t guarantee claims will be paid, and don’t need to be regulated. The nonprofits are well managed, according to ministry officials, with third-party audits and a sterling history of sharing members’ claims.
Ministries generally don’t allow members to sue and require disagreements to be settled by arbitration and mediation.
Some ministries say they cost about 30% less than private insurance. Monthly payments, or sharing, may range from about $75 for a single person under age 30 to $500 or so for a family.
State regulators also say health ministries disrupt the insurance market because they tend to attract healthier consumers, siphoning them from commercial plans that can be left with sicker or older customers. Most ministries don’t always share bills for certain pre-existing conditions, whereas the ACA requires insurers to cover anyone regardless of their past or current medical history.
“They [ministries] have the potential to destabilize the market by drawing off the good risk,” said Mike Kreidler, Washington’s state insurance commissioner.
Monday, January 4, 2016
Doctors Vs. Bureaucrats
Dr. Marion Mass asks, "When will more Doctors stand up for their Patients and Themselves?"
An excerpt:
An excerpt:
Let’s get back to what really matters: the patient. At the moment I heard about not having crucial antibiotics for a sick infant, I snapped. I walked to the nearest phone and dialed the pharmacy, “Dr. Mass here. Why is patient x waiting for meds?”………(party line reply delivered)….”I see. You are going to mix up the antibiotics and get them to the ER in ten minutes. Otherwise, I will call the hospital CEO and tell him that I am going to tell the parents that their child is in danger because of hospital policy. I will not have some (un-publishable word) bureaucrat dictate my patient’s care. What? …Oh, thank you.” Coming clean to let you know how fun and liberating that moment was, as the ER staff stared at me in shock.Read the whole thing. (Via Dr. Megan Edison.)
I don’t wonder why more physicians don’t complain; it takes time. We are knee deep in CME, MOC, state and hospital mandates, insurance company fights, on and on. No wonder patients say we don’t take enough time with them. Furthermore, 80% of physicians are hospital-employed. Buck the system, lose a job. If you aren’t hospital-employed, you are bogged down keeping your indie practice alive for the sake of the patients you love...
Tuesday, December 22, 2015
Kids and Concussions
From MIT Technology Review: "Are Young Athletes Risking Brain Damage?"
And with the increasing awareness of concussion injuries, comes a rise in bogus (or marginal) services.
And with the increasing awareness of concussion injuries, comes a rise in bogus (or marginal) services.
Monday, December 21, 2015

Friday, December 18, 2015
Politics and Health
This New York Times column by Dr. Aaron Carroll acknowledges an important truth: "Even in Basic Health Decisions, You Can’t Screen Out Politics".
Whenever people expect "somebody else" to pay for their health care, then inevitably "somebody else" will decide what care they will (or will not) receive.
This is also why I support health reforms that allow patients to control as much of their own health spending as possible (such as Health Savings Accounts, direct pay primary care, and catastrophic-only insurance with as few mandated benefits as possible.)
Tuesday, December 15, 2015
Hsieh Forbes Column: Are Mandatory Electronic Medical Records Causing Doctor Burnout?
I've expanded my latest blog post into a new Forbes column: "Are Mandatory Electronic Medical Records Causing Doctor Burnout?"
In this piece, I discuss why both doctors and patients are frustrated with electronic medical records (EMRs), drawing upon good reporting from the Chicago Tribune and the Wall Street Journal. I also discuss some ways patients can act to protect the quality of their health care, despite the problems caused by the EMRs.
Thanks to Dr. Matthew Bowdish for alerting me to the WSJ piece.
Bonus: I managed to violate Betteridge's Law of Headlines!

Mandatory Electronic Records and Doctor Burnout
Detailed piece in the 12/12/2015 Chicago Tribune: "Beleaguered by electronic record mandates, some doctors burning out".
One excerpt:
Imagine if the government mandated electronic accounting software for all small businesses for billing and inventory, regardless of whether or not a particular business found it worthwhile. Or if the government mandated universal smartphone ownership, whether or not an individual needed those capabilities. Such mandates would have a hugely distorting effect on the quality and usability of the product.
Image below from the article: "Dr. Niva Lubin-Johnson, an internist, walks with her laptop to see a patient Dec. 8, 2015, at her practice in Chicago's Chatham neighborhood. She is unhappy with federal requirements for electronic health records. (Zbigniew Bzdak / Chicago Tribune)"

One excerpt:
There are so many boxes to click through, she [Dr. Niva Lubin-Johnson] wonders whether she spends more time with her patients or with her computer. She's had to cut back from seeing four patients an hour to three so she doesn't feel overwhelmed. When she does examine patients, she also spends much of her time on her laptop, filling out dozens of electronic forms mandated by law.The concept of electronic medical records is good. But these were never adopted in an organic fashion by physicians and hospitals choosing in a free market which systems to purchase, based the feature sets that helped them and their patients. Rather, they were rammed down doctors' throats via government carrots-and-sticks. Vendors essentially had a captive audience.
"Is this really helping us with patient care? The answer is no. We're just checking off boxes, sending in a report," said Lubin-Johnson, 58.
It's getting to the point where she is looking forward to retiring. It's a thought she rarely entertained before the federal government began requiring physicians to use an elaborate — or maddening and onerous — system of electronic health records four years ago or face penalties worth tens of thousands of dollars in lower Medicare reimbursements.
Imagine if the government mandated electronic accounting software for all small businesses for billing and inventory, regardless of whether or not a particular business found it worthwhile. Or if the government mandated universal smartphone ownership, whether or not an individual needed those capabilities. Such mandates would have a hugely distorting effect on the quality and usability of the product.
Image below from the article: "Dr. Niva Lubin-Johnson, an internist, walks with her laptop to see a patient Dec. 8, 2015, at her practice in Chicago's Chatham neighborhood. She is unhappy with federal requirements for electronic health records. (Zbigniew Bzdak / Chicago Tribune)"
Thursday, December 3, 2015
They Did WHAT To Revive People In The 18th Century ?!?
From Neatorama: "This Emergency Enema Kit Was the Defibrillator of the 18th Century".
I am so very, very, very, thankful that we've progressed past this point:

I am so very, very, very, thankful that we've progressed past this point:
According to Eighteenth Century British medicine, that it was possible to revive a person who had stopped breathing by blowing tobacco smoke up his rectum. Emergency enema kits like these were the defibrillators of the day: essential lifesaving tools designed by medical professionals. Ella Morton of Atlas Obscura writes:I'm surprised this hasn't been on an episode of House, MD.
Cardiopulmonary resuscitation, or CPR, was still centuries away from common usage. Instead of pumping the chest or giving mouth-to-mouth to a drowning victim—a practice that prominent British doctor William Hunter called "vulgar" in 1776—rescuers employed a variety of other dubious methods when attempting to revive those with waterlogged lungs. Rubbing the skin, inflating the lungs via a tube inserted into the trachea, and bloodletting were among the approaches. The most creative technique, however, was rectal tobacco insufflation—piping smoke into the unconscious person’s intestines via a bellows inserted in the anus.Occasionally the process worked. The medical journal The Lancet repeats a story from 1746:
A man's wife was pulled from the water apparently dead. Amid much conflicting advice, a passing sailor proffered his pipe and instructed the husband to insert the stem into his wife's rectum, cover the bowl with a piece of perforated paper, and ‘blow hard.’ Miraculously, the woman revived.
Wednesday, December 2, 2015
Your Doctor Doesn't Want to Hear About Your Fitness-Tracker Data
Basically, it's the medical version of TMI -- "Your Doctor Doesn't Want to Hear About Your Fitness-Tracker Data":

Wearable producers such as Apple, Fitbit, and Pebble will ship more than 76 million of the devices by the end of the year, according to market research firm IDC. Some doctors and researchers, however, remain unimpressed, They question the value of the particular metrics tracked, as well as the validity of the deluge of data these gadgets produce...
Monday, November 30, 2015
Hsieh Forbes Column: Why You Want Your Doctor To Be Wrong (Sometimes)
My latest Forbes piece is now out, "Why You Want Your Doctor To Be Wrong (Sometimes)".
Here is the opening:
For more details, read the full text of "Why You Want Your Doctor To Be Wrong (Sometimes)".
And my personal favorite example of Type 1 vs. Type 2 errors is below:

Here is the opening:
“Mommy, my tummy really hurts!”I discuss Type 1 vs. Type 2 errors, why they are important, and why certain kinds of diagnostic errors are not merely unavoidable but (in the right context) desirable.
Your 7-year old daughter wakes you up in the middle of the night, doubled over in pain. You take her to the local ER. The on-call surgeon, Dr. Smith, performs a thorough physical exam, reviews the test results, informs you that she has appendicitis, and says she needs surgery right away. You sign the consent forms, and he whisks her off to the OR. An hour later, Dr. Smith comes back and says, “I’m sorry. We removed her appendix, but it turned out to be normal. She didn’t have appendicitis, just a severe case of gastroenteritis or ‘stomach flu’.”
Should you be relieved or angry? Did Dr. Smith make a mistake? Did he perform an unnecessary operation?...
For more details, read the full text of "Why You Want Your Doctor To Be Wrong (Sometimes)".
And my personal favorite example of Type 1 vs. Type 2 errors is below:
Monday, November 23, 2015
Thursday, November 19, 2015
When Unethical Medical Experiments Bear Fruit
I'm not a utilitarian, and the medical experiments described below were truly appalling.
But there is some informative medical history in this piece: "These medical experiments were horrible, unethical — and useful".
People can debate some of the fine points of the current system of IRB (Institutional Review Board) approval and informed consent for medical experiments. But the current system is far better than what has occurred in the past.
Tuesday, November 17, 2015
Short Story: SMOD 2016
I'm exercising blogger's privilege to post something totally unrelated to health care policy.
Here's my latest short story, "SMOD 2016" (400 words). FYI, it's a little dark, in the spirit of Frederic Brown.
Here is the opening:
Read the rest at: "SMOD 2016".
["Asteroid Belt", image courtesy Wikipedia.]

Here's my latest short story, "SMOD 2016" (400 words). FYI, it's a little dark, in the spirit of Frederic Brown.
Here is the opening:
SMOD 2016
A short story by Paul Hsieh
"So, basically you're saying that humanity should be extinct by now." MIT astrophysics professor Linda Tsang furrowed her brow.
"Yes, many times over," replied statistics professor Max Wendt. "Based on the new telescope data you provided me about the asteroid belt, the Earth should have been struck by a 'Dinosaur Killer' rock at least 5 or 6 times in the past 10,000 years."
"So, why haven't we?" asked Tsang.
"Well, there are a few possibilities," said Wendt...
Read the rest at: "SMOD 2016".
["Asteroid Belt", image courtesy Wikipedia.]

Monday, November 16, 2015
The Inadequacy of 15-Minute Medicine
In the Washington Post, Dr. Michael Stein writes: "When medical care is delivered in 15-minute doses, there's not much time for caring".
Dr. Stein's bottom line:
One excerpt:

Dr. Stein's bottom line:
My job, in its barest 15-minute form, is to separate the serious possibilities from the less serious, offer a diagnosis and an explanation, recommend any additional testing and list the possible courses of action. But a hurried, task-oriented approach doesn’t accommodate the meandering, overlapping, widening issues of patients. It undermines kindness. And it prevents doctors from being what our patients hope we will be when they walk in: unrushed explorers on the lookout for the next discovery.Fortunately, patients and doctors can avoid these problems through a "direct pay" or "concierge" model, as discussed in my earlier Forbes piece, "Is Concierge Medicine The Correct Choice For You?". Doctors can take the time to give the patients' issues the attention they need.
One excerpt:
In response to this frustrating situation, more doctors are seeking an alternative practice model. They are establishing “concierge” or “direct pay” practices, where patients pay a monthly or annual fee for enhanced services, including same day appointments, 24/7 access to their doctor, e-mail consultations, and longer appointment times. Instead of the usual rushed 10-15 minute appointments, these doctors typically offer 45-60 minute visits allowing them to really delve into their patients’ problems and craft individualized treatment and prevention plans.(Washington Post link via Dr. Matthew Bowdish.)
The Indianapolis Business Journal described how concierge medicine helped patient Dale Sventeck. Sventeck suffered from a “frozen shoulder” which severely limited his range of motion. Most doctors he saw simply wanted to schedule him for an MRI study and surgery. But concierge physician Kevin Logan was able to take the time to diagnose that Sventeck’s problem was caused by the mercury in his dental fillings. Dr. Logan advised Sventeck to remove the fillings. One month later, his shoulder was back to normal.

Thursday, November 5, 2015
Sissel Lawsuit Update
Matt Sissel has an OpEd in the 11/3/2015 Washington Times on his anti-Obamacare lawsuit: "Taking a stand against Obamacare".
Sissel is being represented by Timothy Sandefur of the Pacific Legal Foundation (PLF). For more details, see the PLF page on the case.
I wish them both success in their fight for individual rights!

Sissel is being represented by Timothy Sandefur of the Pacific Legal Foundation (PLF). For more details, see the PLF page on the case.
I wish them both success in their fight for individual rights!
Monday, November 2, 2015
NEJM On Peer Review Fraud
New England Journal of Medicine: "Peer-Review Fraud -- Hacking the Scientific Publication Process".
Fraudulent reviews on Amazon or Yelp are bad enough. Fraudulent peer review in science and medicine could be very, very dangerous to patients.
Fraudulent reviews on Amazon or Yelp are bad enough. Fraudulent peer review in science and medicine could be very, very dangerous to patients.
Subscribe to:
Posts (Atom)